Pain in an emergency setting shows up with untidy context. It appears caught under control panel plastic, in a rugby shoulder half out of its socket, in a dialysis client with a hip fracture on blood thinners, or in a baffled elder who can not find the right words. The distinction in between a disorderly scene and a controlled handover usually boils down to two points: just how well you can analyze discomfort, and just how deftly you can handle it without making the patient even worse. PUAEME008, generally called Offer Discomfort Management, exists for that exact factor. It distills core emergency pain administration skills into a concentrated, functional framework that uses across paramedicine, initial feedback, nursing outreach, and allied health in field environments.
I have actually taught and used this web content in contexts that ranged from city road injury to remote mine websites. What follows is a based, practitioner's review of PUAEME008 supply pain monitoring, with enough information to help you evaluate whether a discomfort management program or pain administration certification training course based on this system is appropriate for you or your team.
What PUAEME008 really covers
At its heart, the system builds competence in three domain names: secure analysis, efficient analgesia selection and distribution, and recurring review with documents. Unlike broader pain monitoring programs that dive deep into chronic discomfort concept or multispecialty pathways, this is emergency situation pain monitoring. The focus rests directly on quick assessment, fast-acting treatments, and watchful monitoring.
Most service providers provide PUAEME008 as a short program in pain administration that runs 6 to ten hours of face-to-face time plus pre-reading, with hands-on method threaded via instance scenarios. The entry bar varies somewhat by jurisdiction and employer, yet candidates are normally existing initial -responders, firemens, lifesavers, or wellness workers with some medical exposure. The certification training course suffering management at this degree is not an alternative to paramedic training nor a certificate for independent numbing management. It furnishes you to add to much better analgesic treatment within your scope, and to function securely under local protocols.
Common capabilities evaluated under PUAEME008 provide pain monitoring include: performing pain evaluations using standard tools, acknowledging warnings that require immediate escalation, selecting non-pharmacological methods, and carrying out permitted medicinal representatives under direction or protocol. It also includes post-intervention testimonial, negative effects administration, and clear handover.
The real worth of structured assessment
When a person winces and grabs their ribs, it's alluring to go directly for the gas or the IV. Resist that impulse. A structured evaluation typically conserves time and prevents blunders. In practice, I anchor my approach on a simple set of three: mechanism, pattern, risk.

Mechanism keeps you truthful concerning what forces were involved. A low-speed autumn onto an outstretched hand can pain management courses for nurses still trigger a scaphoid crack with stealthily subtle indicators. A rollover collision suggests multi-system injury till tested or else. Pattern asks exactly how discomfort behaves gradually and with motion. Is it sharp, throbbing, burning? Does it emit? Is there disproportionate pain to light touch that means area syndrome? Danger concentrates on the person's physiology and context: anticoagulants, kidney illness, respiratory concession, previous analgesic allergic reactions, intoxication, or language barriers.
I still utilize the 0 to 10 mathematical score scale because it works throughout ages and cultures far better than any kind of choice. For nonverbal patients, the Faces Pain Range or observational devices like the FLACC (face, legs, activity, cry, consolability) rack up help convert behavior into a functional measure. What issues is not the solitary rating, but the fad and correlation with your interventions.
Small information pay dividends. Ask, "What would be an appropriate discomfort degree for you today?" Numerous people will certainly state three or 4. That becomes your real target, not an academic zero. Clarify what they have currently taken, including over the counter medications, so you do not pile doses inadvertently. File the time, dose, route, and person response in a manner that transfers conveniently to the obtaining team.
Non-pharmacological actions that actually work
People discount non-drug techniques because they appear soft. Succeeded, they are rapid and powerful, and they lower the amount of medicine required. I have viewed a crack person go from a discomfort score of 8 to five within two minutes just by improving splinting and making use of training strategies for breathed in pain management training for nurses analgesia.
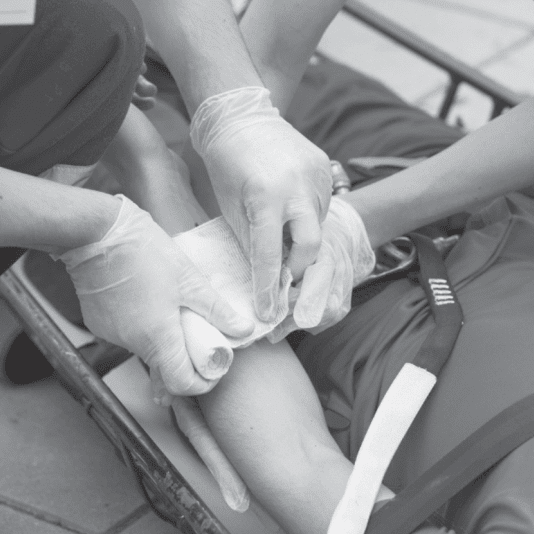
- Rapid positioning and immobilization: Reposition to comfort early, not after you've established all the tools. Splint joints over and below a suspected fracture. For shoulder misplacements, a straightforward sling and swathe minimizes muscle convulsion and secures neurovascular structures. Ice or warm: In the area, ice is a lot more readily available and dependable. Cover it to stay clear of skin injury. Ten to fifteen minutes gets time and assists with swelling. Pressure and elevation: Venous slime responds to stress. A sprained ankle responds to gentle compression and altitude if it doesn't intensify pain. Guided breathing and mentoring: When making use of inhaled analgesia, don't simply hand the gadget to the individual. Show, after that instructor a constant cadence of breaths. Patients that hyperventilate via discomfort waste the advantage, so maintain them paced and engaged. Environmental control: Lower brilliant lights and noise. Provide the person a feeling of control by explaining what you're doing following. That alone reduces anxiety-driven pain amplification.
These tactics are core to emergency situation pain administration since they are safe across a large range of problems and can be started instantly, also while pharmacology is being prepared.
Pharmacological options within scope
Medication choices in PUAEME008-aligned discomfort monitoring training differ by regional procedures, however normally consist of clear support on three classes: inhaled anesthetics, oral non-opioids, and, in some services, parenteral choices under direction.
Inhaled methoxyflurane continues to be a favored in Australian pre-hospital look after moderate acute pain. The beginning fasts, the tool is portable, and the titration is patient-driven. It is not for everybody, specifically if there are contraindications like renal disability or hypersensitivity, and you must value optimum dose restrictions. Coaching method figures out effectiveness greater than several recognize. If the client takes superficial, irregular puffs, they will certainly report "it's not working." A tranquility, constant inhale with the exhaust properly fed on gives regular relief.
Oral anesthetics such as paracetamol and NSAIDs are usually secure and reliable when the patient tolerates oral consumption and there are no warnings like suspected GI blood loss or renal concession. The catch is dose piling since individuals self-medicate prior to you get here. Verify timing and amounts. For a lengthy transfer, early oral agents can smooth the trip, while you layer various other methods on top.
Opioids demand respect. In some setups, the device of competency permits administration under professional administration, standing orders, or direct guideline. The debates around opioids in some cases overshadow their genuine role in injury and severe sharp pain. The compromises are simple: use the most affordable efficient dose, see the respiratory rate and psychological standing, and treat nausea proactively when suitable. Naloxone must not be a theoretical idea; be qualified in its usage. If you do not have permission for opioids, concentrate on optimizing what you can do, and rise early to teams who can bring them.
Adjuncts like ketamine being in sophisticated methods rather than standard PUAEME008, but you need to understand their location. Dissociative analgesia helps in caught individual extrication or major fracture reduction when opioids alone fall short, with a security profile that preserves air passage reflexes oftentimes. This is not an informal add-on. It needs training, tracking, and a team comfortable with the psychoperceptual results that can agitate both client and provider.
Safety, contraindications, and the art of saying no
One of the hardest abilities to instruct is not what to provide, however when to hold back. Discomfort relief need to never ever obscure the diagnostic photo in time-critical conditions, and some methods just enhance risk.
Examples that require care or alternatives:
- Abdominal discomfort with peritonism: gentle titration is great, but avoid deep sedation that could mask wear and tear prior to medical review. Head injuries with transformed level of consciousness: focus on air passage and perfusion. Sedation can cloud neurologic evaluation, so titrate moderately and record standard GCS with succeeding changes. Hypotension or shock: opioids can go down the high blood pressure additionally. Maintain perfusion initially. Take into consideration breathed in alternatives or non-pharmacological procedures while addressing the cause. Late pregnancy: examine medicine security for both mommy and unborn child. Position left side to minimize aortocaval compression. Renal or hepatic illness: dosages and options change. NSAIDs commonly relocate off the table in kidney compromise. Methoxyflurane is contraindicated for those with recognized kidney impairment in many protocols.
Saying no is simpler when you can state yes to another thing. Offer ice, immobilization, peace of mind, and time-limited breathed in analgesia while you intensify care or look for clinical direction.
Documentation that helps the following clinician
A great handover is a treatment treatment in its very own right. The getting team's capacity to proceed risk-free analgesia rests on what you share. I make use of a mental template: what hurt, how much, what transformed, what we offered, what occurred next.
Include device, pain rating pattern, relevant comorbidities, allergies, and specific drug information with time marks. If a client records adverse effects such as nausea or dizziness, include that. When non-pharmacological actions aid, state so, due to the fact that it establishes the assumption for continued usage in the ED.
Clear paperwork is crucial for any kind of discomfort monitoring certificate, both as an evaluation requirement and as a professional practice. It secures the patient first, and it secures you.
Communication and permission under pressure
Emergency scenes are noisy, disorderly, and frequently public. Pain magnifies fear, and worry can either rise or settle depending on your communication design. Begin by naming what you see. "I can see your ankle is inflamed and that activity really hurts. I'm mosting likely to assist you obtain more comfortable." Then clarify the plan in short, concrete steps. Deal choices when possible. "We can utilize a quick inhaled pain relief now while we prepare a splint. Would certainly you such as to try that?" Clients that really feel a feeling of company commonly need less drug and work together even more totally with immobilization and transfer.
Informed approval in the field implies ordinary language and comprehension checks. If the person is not capable, work under suggested approval within your procedures and record the rationale. For children, involve caregivers while preserving main focus on the kid's comfort and safety. For non-English audio speakers, use interpreter solutions if readily available by phone, or lean on visual demos and tranquil pacing.
Scenarios that examine judgment
The value of discomfort administration training courses becomes apparent in edge situations. A few that reoccur in evaluations and the real world:
- The entraped vehicle driver with pelvic pain and dropping blood pressure. Your ideal analgesic could be a pelvic binder used early, with cautious titration of breathed in or IV agents while you reduce activity. If ketamine is within your range, it can support extrication without deep respiratory clinical depression. Over-sedation in a restricted area transforms a rescue right into an airway emergency. The elderly person with a neck of femur fracture that is tough of hearing and anxious. Mild description, cozy coverings, a scoop with cushioning, and breathed in analgesia usually outperform rushing for an IV in a confined bedroom. If you have fascia iliaca block capacity by means of an advanced pathway, the relief can be transformative, yet it rests beyond the typical PUAEME008 scope. The rugby player with a shoulder dislocation and vasovagal propensity. Set them semi-recumbent, instructor their breathing, give breathed in analgesia, and debilitate. If moving isn't in your scope, don't try to be a hero on the sideline. Good discomfort control and secure transfer defeated a dangerous attempt. The well-known opioid-tolerant patient with a serious limb injury. Standard dosages may do little bit. Pile modalities: ice, splinting, inhaled analgesia, and, if accredited, greater yet thoroughly titrated opioid dosing with close tracking. Establish expectations that full relief may not be feasible, but purposeful decrease is. The youngster with a forearm crack. Youngsters respond wonderfully to great splinting, interruption, and breathed in analgesia. Let them experiment the gadget. Invite a caregiver to sit at eye level and mirror the breathing pattern.
These situations expose the core reality: method understanding issues, therefore does judgment. PUAEME008 trains both, using simulation and responses as opposed to memorizing checklists alone.
Monitoring and reassessment: capturing problems early
Analgesia does not finish with administration. Efficient emergency situation discomfort monitoring suggests you look for both healing result and side effects. Track respiratory system rate, oxygen saturation if offered, level of consciousness, and discomfort rating at practical intervals. Use your eyes and ears. A patient whose sentences reduce between breaths is refraining fine, also if the monitor looks stable.
Nausea prevails after opioids and in some cases after breathed in agents. Treat early when procedures enable, provide emesis bags, and safeguard the respiratory tract. It is far better to offer an antiemetic than to remove a mask mid-transport to manage abrupt vomiting.
Over-sedation requires swift, crucial action. Promote, sustain ventilation with respiratory tract adjuncts and bag-mask if required, and consider reversal representatives when in scope. Record the sequence clearly. Prevent the catch of going after sleepiness with duplicated turnarounds that speed up serious pain and anxiety unless airway security demands it. Aim for a safe happy medium where the person is arousable and breathing well.
Competency, accreditation, and where this suits your career
For many carriers, PUAEME008 is a tipping stone instead of a location. As a pain monitoring certificate program, it licenses practical capacity at the sharp end of treatment. It sets perfectly with sophisticated trauma treatment modules or with professional discomfort monitoring programs for registered nurses and pain monitoring programs for physio therapists who run in intense setups like ED triage, outreach clinics, or sideline and event medicine.
If you are going after a discomfort management accreditation in a wider feeling, recognize the landscape. There are discomfort administration training programs that concentrate on chronic and multidisciplinary treatment, incorporating psychology, rehab, and interventional procedures. Others, like PUAEME008 offer pain administration, laser know frontline, short, scalable abilities. Both have worth, but they offer different troubles. A medical professional who consistently deals with frailty fractures in a neighborhood hospital may benefit from both: emergency situation pain abilities for the preliminary stage, and chronic pain expertises for the weeks that follow.
For registered nurses, pain management training for registered nurses built on this system improves triage performance, person fulfillment, and security with standing orders. For physio therapists, discomfort management courses for physio therapists that include acute injury assessment and non-pharmacological approaches enhance manual therapy skills and enhance sideline and clinic decisions. Companies frequently appreciate the mobility of a discomfort monitoring certification course that aligns with acknowledged expertises, specifically when onboarding mixed teams for events or remote postings.
Training style and what to try to find in a provider
Not all discomfort administration training is developed equal. Seek a program that highlights hands-on experiment practical situations. You need to entrust to muscle mass memory around inhaled gadget arrangement, splinting, risk-free training and positioning, and the choreography of offering pain relief while taking care of scene logistics. Simulated clients who can offer feedback on communication add value, because tone and pacing change outcomes.
Quality service providers update web content as methods progress. Ask just how they take care of scope differences in between regions, and whether they supply pathway-specific alternatives. Seek organized analysis that includes created understanding checks and observed practicals. A good course balances the checklist with mentoring and judgment. If the class is primarily glides regarding pain theory without device handling, you will certainly not prepare when it is dark, raining, and your patient is wedged under a fence.
For those time-poor and balancing rosters, short programs hurting monitoring that blend pre-course eLearning with a focused in-person laboratory are reliable. Validate that the discomfort monitoring certificate straightens with your service requirements and that the issuing body is identified for compliance and audit purposes.
Legal, honest, and social considerations
Pain is universal, but our feedbacks to it are not. Social norms form exactly how individuals express pain and what they get out of care. Some under-report pain to show up calm. Others utilize vibrant expressions that check out as distress yet reflect cultural idiom. Listen more than you talk, and stay clear of labeling people as "medicine seeking" in acute contexts based upon expression alone. Your documentation ought to be accurate: observed habits, reported discomfort, treatments, and response.
Legally, practice within your scope and your service's scientific governance. Shop and get rid of dangerous drugs according to policy. Videotape set numbers and wastage where needed. If standing orders require notice to a clinical police officer, do it and log the time. These are not governmental obstacles. They are safeguards that maintain you and your people safe.

Ethically, make the patient comfy while shielding future diagnostic quality. We can eliminate enduring without covering up the signs we require. The more exact your paperwork and review, the easier this equilibrium becomes.
Building an individual toolkit
Every company develops a small collection of routines and devices that make discomfort management smoother. Mine includes pre-charged inhaled analgesia kits, two dimensions of slings conveniently available, soft extra padding for splints, spare emesis bags clipped where I can reach them with one hand, and a mental manuscript for mentoring breathing that I can supply even when the scene is noisy. I practice the manuscript until it is automatic. "I'm mosting likely to help you take slow-moving, deep breaths using this mouth piece. Breathe in as I count to 3, hold for a moment, after that out. Let's do 3 together." It appears basic, yet it keeps me and the patient in sync.
I also maintain a firm practice of checking the moment before and after each treatment and stating it out loud for the record. "Methoxyflurane began at 14:36." The behavior develops much better notes and tighter care.
Where PUAEME008 beings in the larger picture
If you zoom out, discomfort administration training is not concerning going after ratings down to absolutely no. It is about feature, security, and self-respect. An individual who can tolerate a move from flooring to stretcher without wheezing or safeguarding is much less most likely to undercut during transfer. A child that trusts you with the mouth piece will approve a splint and allow an IV without a struggle. A senior that recognizes why the area is kept quiet and dim might clear up enough to relieve muscle stress and reduce requirement for sedation.
PUAEME008 is a focused system, however it punches over its weight due to the fact that it alters the pace of care. When you obtain the first ten mins right, everything downstream has a tendency to go better: more clear medical diagnoses, less difficulties, shorter ED keeps. That is why employers typically prioritize a pain administration certificate in onboarding for occasion medicine teams and remote responders, and why refresher training yearly or two makes good sense even for seasoned clinicians.
Final ideas for possible learners
If you are considering an offer discomfort administration program against other completing needs, look at your common instance mix and your weak spots. Do you wait with inhaled devices? Do you fumble splints under pressure? Do you document the pattern, or simply the dose? A good discomfort monitoring training course will tighten up those links in your chain. If you plan to relocate into innovative duties, the certification supplies a clean foundation for additional authorizations and advanced modules.
For teams, train with each other. Pain relief works best when everybody knows their role: that trains breathing, that handles the splint, that documents, and who watches the monitor. Rehearse transfers in confined areas, in reduced light, and with simulated tools failings. Those representatives repay when the phone call comes and the individual is counting on you to bring not just the medications, yet the calm.
Emergency pain administration is a craft. PUAEME008 provides you the necessary devices, however craft originates from use. Pick them up, method intentionally, and then go make tough moments easier for individuals that meet you on bad days.